Loading
Old version — revision 2
This is a fixed snapshot of Electrocorticography interfaces, saved by Import. It is not edited and it is not updated; the article may have changed since.
Edit summary: Re-import of content/ecog-interfaces.md — the file changed after the initial import. Not an edit.
Read the current versionWhat this revision changedAll 2 revisions
Electrocorticography interfaces
Brain-computer interfaces that record from electrode arrays resting on the cortical surface rather than penetrating it, trading single-neuron resolution for stability and coverage.
TechnologyEmerginglate 2020sTRL 6revision 2
12.8 kB1,148 wordsCyberneticsfrontmatter date 2026-10-29
Electrocorticography interfaces are brain-computer interfaces that record from electrode arrays laid on the surface of the cortex, either beneath the dura (subdural) or on top of it (epidural), without penetrating brain tissue. They sit in the middle of the invasiveness range. Their spatial and spectral resolution is better than scalp electroencephalography and worse than a penetrating Utah array, and their mechanical stability is better than either.
The technique exists because neurosurgery needed it first. Grids of platinum contacts have been placed on the cortex for decades to localize seizure onset and map eloquent cortex before epilepsy surgery. The field therefore inherited a large clinical base of patients temporarily instrumented with electrodes and willing to take part in research, and most of what is known about how speech is represented in human cortex comes from that population.
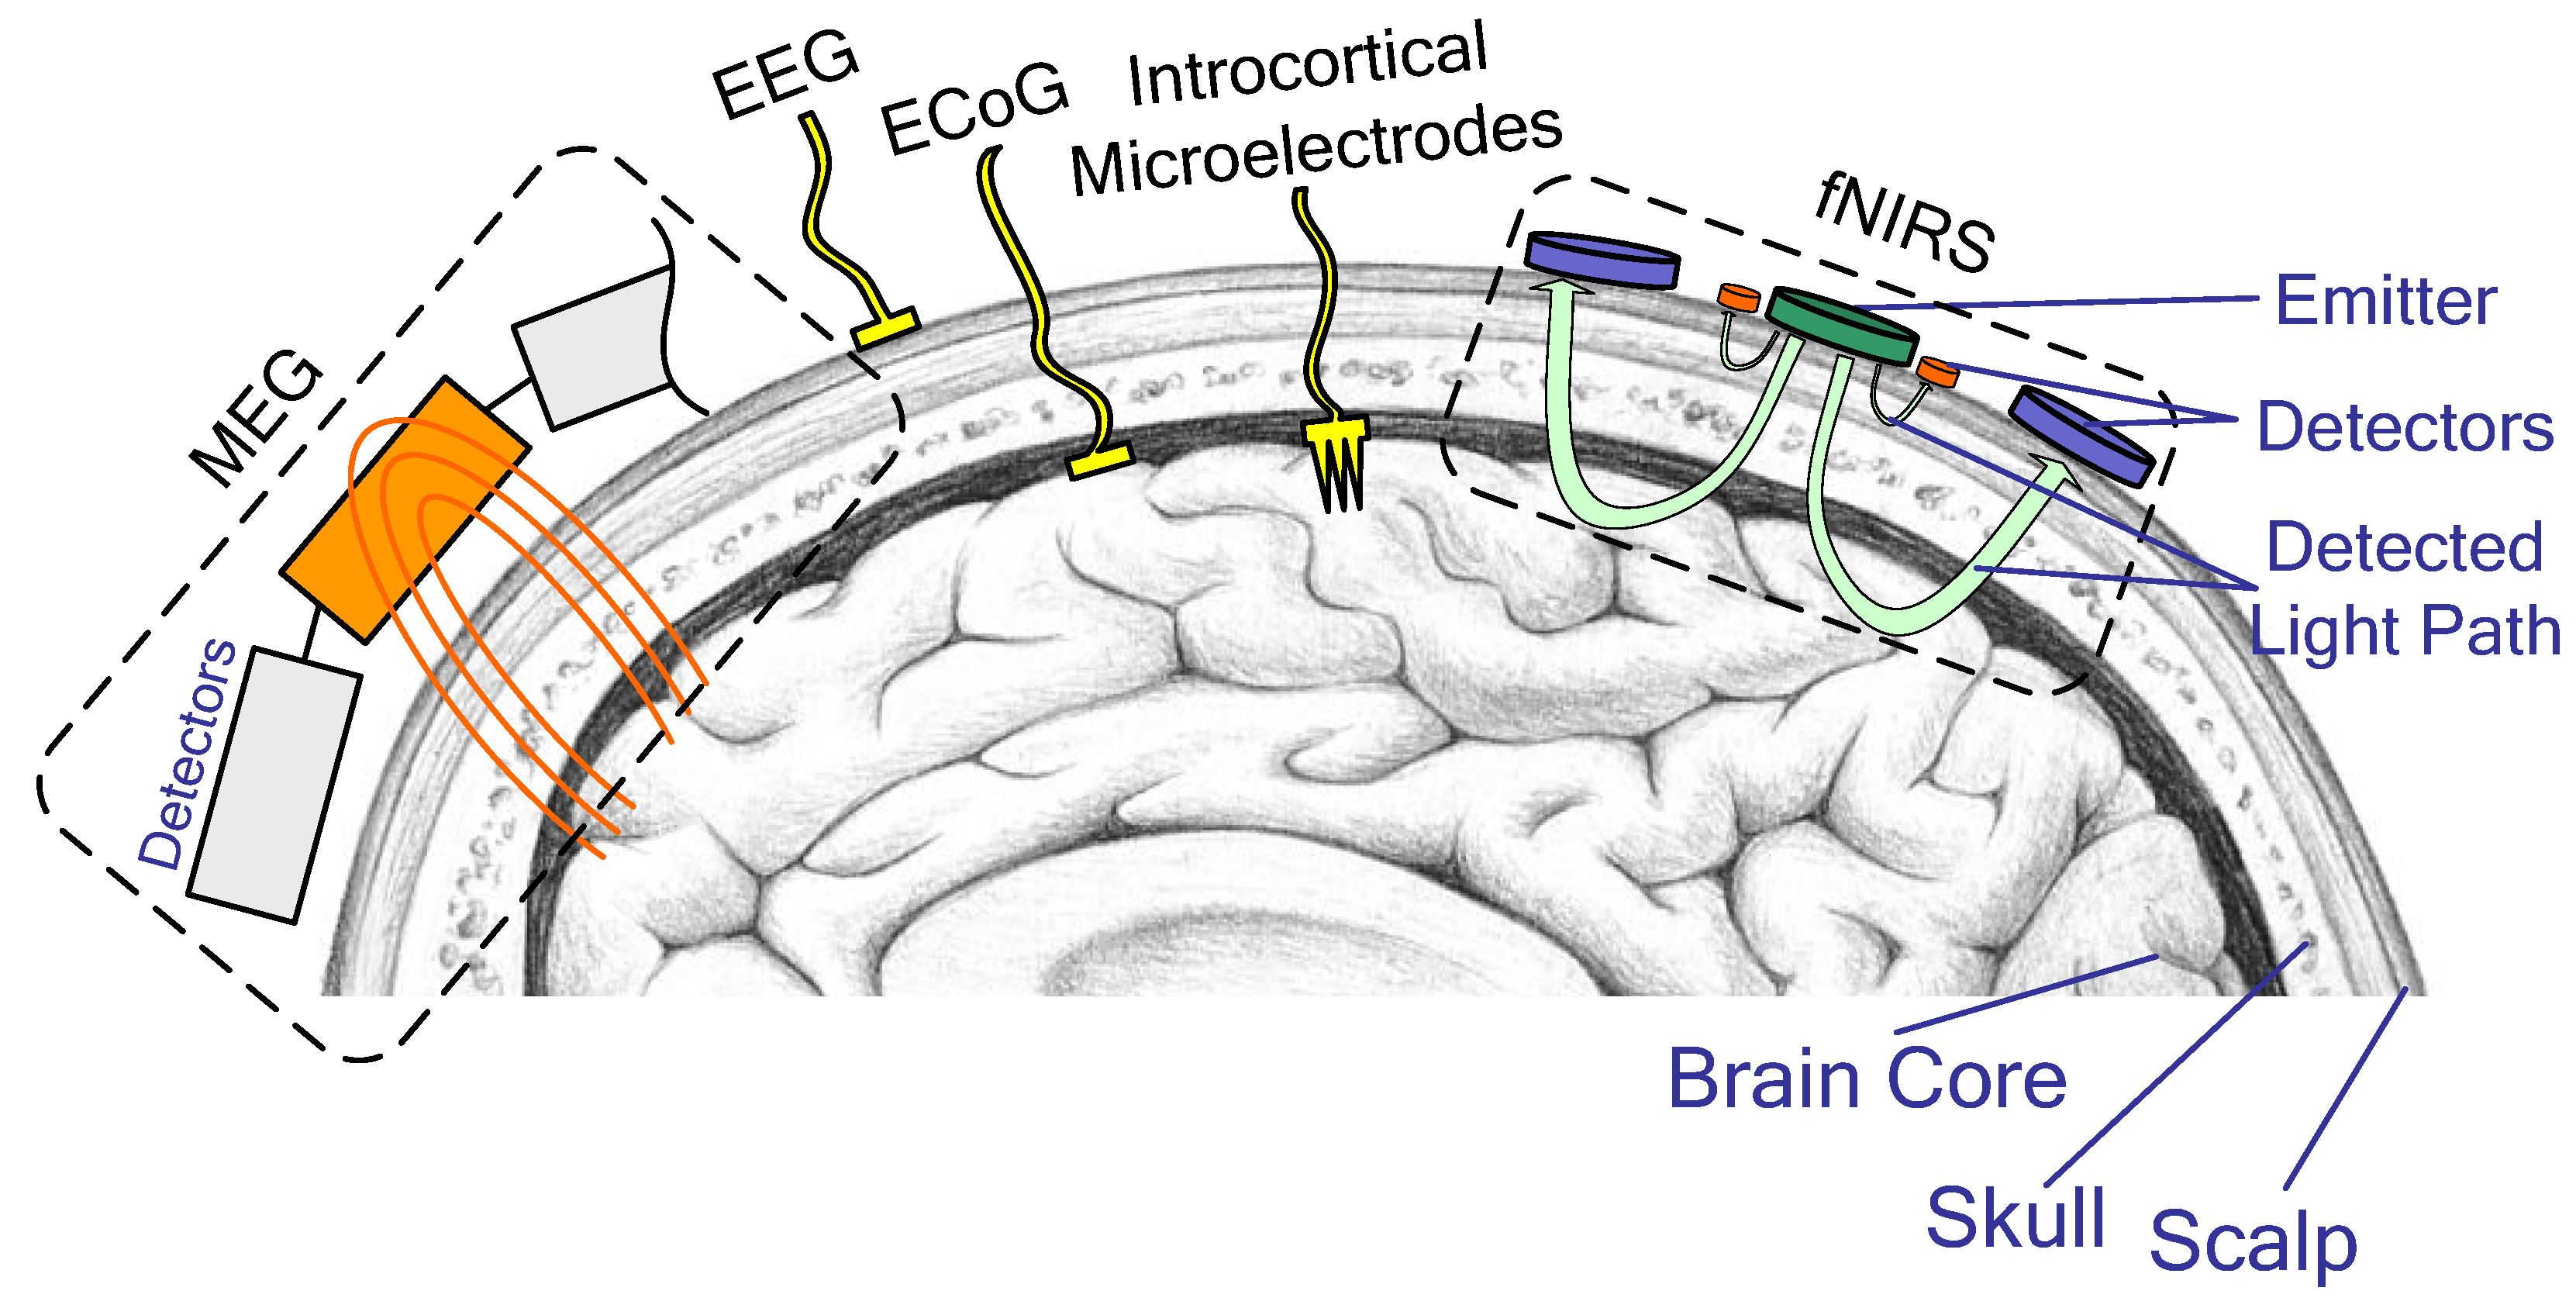
How it works
A standard clinical grid is a silicone sheet holding platinum discs a few millimetres across on a one-centimetre pitch. Research arrays go finer. High-density grids use a two to four millimetre pitch, and thin-film micro-electrocorticography arrays carry hundreds or thousands of contacts at sub-millimetre spacing on a substrate thin enough to conform to the cortical surface, including into sulci.
The most useful feature for a Brain–computer interface is high-gamma power, roughly 70 to 200 hertz. Broadband high-frequency activity recorded at the surface correlates well with the firing rate of the population of neurons directly underneath, so it works as a proxy for local spiking that can be measured without pushing anything into the tissue. Lower-frequency rhythms carry complementary information about state and movement preparation. Together these features feed standard Neural decoding pipelines.
Because the array does not penetrate, it does not sever capillaries or provoke the encapsulation response that displaces neurons from a penetrating tip. Fibrous tissue does form around a subdural grid, but the recorded signal degrades far more slowly than intracortical spikes do. This is the main engineering argument for the approach.
The resolution ceilingSurface recording cannot resolve individual neurons, and no increase in electrode density changes that. Cerebrospinal fluid and the dura conduct and blur the signal, so what reaches any contact is a weighted sum over a patch of cortex. Denser arrays sample that blurred field more finely, which helps, but the information about individual cells is lost before it reaches the electrode.
Development history
The clinical practice long predates the interface application. Patients admitted for invasive seizure monitoring spend one to two weeks with grids or depth electrodes in place, awake and able to perform tasks, and that window has supplied most of the human cortical physiology behind modern decoders. The same population, instrumented with hippocampal depth electrodes rather than surface grids, supplies the data behind Memory prosthesis research. The arrangement has its own ethical literature. Participants are patients first, recruited during a stressful clinical episode, and the research question is never the reason the electrodes are there.
-
1930s-1950sClinical electrocorticographyWilder Penfield and Herbert Jasper establish intraoperative cortical recording and stimulation mapping at the Montreal Neurological Institute.
-
2004-2010ECoG as a BCI signalGroups working with epilepsy patients show that high-gamma activity from surface electrodes supports rapid, accurate cursor control learned within minutes.
-
2013Multi-dimensional arm controlA participant with tetraplegia controls a robotic arm in three dimensions using a subdural array, demonstrating that surface signals support continuous control.
-
2016Home use in ALSA fully implanted electrocorticography system in Utrecht lets a woman with late-stage ALS select letters at home, remaining functional over years.
-
2019Exoskeleton controlA French team reports a tetraplegic participant operating a whole-body exoskeleton using bilateral wireless epidural implants.
-
2019-2025Speech decodingSuccessive reports from UCSF decode sentences, then conversational-rate text, synthesized voice, and near-real-time streaming speech from surface arrays over speech motor cortex.
-
2023Brain-spine interfaceEpidural cortical implants drive a spinal stimulator to restore volitional walking after spinal cord injury.
Speech and communication
Surface arrays have dominated speech decoding for an anatomical reason. The representations of the lips, jaw, tongue and larynx are laid out across several centimetres of ventral sensorimotor cortex on the lateral surface of the brain. A large, shallow, two-dimensional map of this kind is what a conformal grid samples best. Penetrating arrays sample it densely within a few square millimetres, whereas a grid samples it sparsely across the whole map.
The line of work from UCSF began with synthesizing intelligible speech from cortical activity recorded during spoken sentences.1 It then decoded attempted words in a man with anarthria after brainstem stroke,2 reached conversational rates with text, synthesized voice and an animated avatar,3 and more recently cut the latency enough for near-continuous streaming output. These results, discussed in detail under Speech neuroprosthesis, come from single participants using research hardware.
Communication systems built on smaller chronic implants have a longer service record. A participant with ALS used a fully implanted system with a small number of surface electrode strips at home to select letters for years, and recalibration drift never became severe enough to stop it working.4 The bit rate was low; the result that mattered was the reliability.
Movement restoration
Surface arrays also drive motor systems. A participant with tetraplegia achieved three-dimensional robotic arm control from a subdural grid,5 and a wireless epidural implant developed in Grenoble allowed a tetraplegic participant to operate a powered Powered exoskeletons, though slowly and under laboratory supervision.6
The most consequential application connects cortex to spinal cord rather than to a machine. In a 2023 report, epidural cortical implants decoded walking intention and drove an implanted epidural spinal stimulator, restoring volitional walking to a man with an incomplete spinal cord injury. He also showed some neurological recovery that persisted with the system off.7 This "digital bridge" framing, in which a BCI reconnects the nervous system to itself rather than to a robot, is now a major direction in Neuroprosthetics.
Advantages and limits
The advantages are stability, coverage and channel scaling. Thin-film arrays can carry a thousand or more contacts without a thousand penetrations, and one company's high-density cortical film received United States clearance in 2025 for temporary use during surgery, a step toward chronic approval. There is a precedent for durability. Deep brain stimulation leads sit in human brains for a decade or more without failing, which suggests that a chronically implanted neural device is not intrinsically impossible and that penetrating recording tips are a particularly demanding case. Flexible penetrating threads of the kind used by Neuralink try to split the difference, accepting penetration while minimizing stiffness.
The limits are structural. Access still requires opening the skull, though narrow-slot and burr-hole insertion techniques reduce the exposure compared with a full craniotomy. Subdural placement carries risks of haemorrhage, infection and cerebrospinal fluid leak, and grids can shift. The resolution ceiling also caps the number of independent control dimensions available. That is why the highest-dimensional results still come from penetrating electrodes, and why the endovascular Stentrode, with far fewer contacts and more distance from cortex, sits lower still.
Any chronic recording of cortical activity, whatever the electrode, produces a data stream from which more can be inferred than the user intends to communicate. That problem is examined under Mental privacy, and it applies with particular force to speech-decoding systems.
Outlook
The plausible near-term path runs through fully implanted, wireless, high-channel thin films aimed at speech loss, where the clinical need is clear and the decoding results are strongest. No current trial is old enough to say whether such devices sustain performance for a decade, or whether the surgery will become routine enough for a neurologist to recommend it to a newly diagnosed ALS patient.
A quieter question is what surface arrays reveal about cortical organization itself. Dense grids over speech and motor cortex have produced maps that animal work could not provide, and those maps feed back into decoder design. The loop between measurement and application resembles the relationship between Connectomics and theories of neural computation.
See also
- Brain–computer interface
- Speech neuroprosthesis
- Utah array
- Stentrode
- Neural decoding
- Neuroprosthetics
- Neuralink
- Mental privacy
References
Footnotes
-
paperAnumanchipalli, G. K., Chartier, J. and Chang, E. F. "Speech synthesis from neural decoding of spoken sentences." Nature, 2019. ↩
-
paperMoses, D. A. et al. "Neuroprosthesis for decoding speech in a paralyzed person with anarthria." New England Journal of Medicine, 2021. ↩
-
paperMetzger, S. L. et al. "A high-performance neuroprosthesis for speech decoding and avatar control." Nature, 2023.↩One participant, severely paralysed after a brainstem stroke; the rates reported are for a decoder trained on her own attempted speech in laboratory sessions.
-
paperVansteensel, M. J. et al. "Fully implanted brain–computer interface in a locked-in patient with ALS." New England Journal of Medicine, 2016.↩A single participant; what the report establishes is sustained unattended home use at a very low bit rate, not decoding performance.
-
paperWang, W. et al. "An electrocorticographic brain interface in an individual with tetraplegia." PLOS ONE, 2013. ↩
-
paperBenabid, A. L. et al. "An exoskeleton controlled by an epidural wireless brain–machine interface in a tetraplegic patient: a proof-of-concept demonstration." The Lancet Neurology, 2019. ↩
-
paperLorach, H. et al. "Walking naturally after spinal cord injury using a brain–spine interface." Nature, 2023.↩A single participant who had already undergone spinal stimulation and rehabilitation, which complicates attributing the residual recovery to the brain-spine link.