Telomeres and telomerase are, respectively, the repetitive nucleotide sequences and associated proteins that cap the ends of linear chromosomes, and the reverse transcriptase that extends them. Telomeres shorten each time a somatic cell divides. When they become critically short, the cell triggers a DNA damage response and enters senescence or apoptosis. Telomere attrition is one of the Hallmarks of aging, but its causal weight in normal human aging is smaller and more disputed than popular accounts suggest.
Structure and function
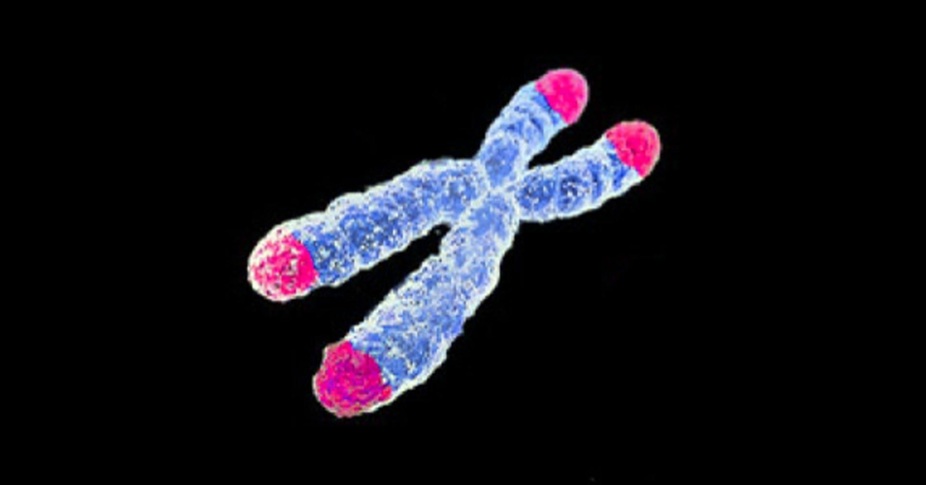
Human telomeres consist of thousands of tandem TTAGGG repeats ending in a single-stranded 3′ overhang, which folds back to form a lasso-like t-loop. Six proteins, TRF1, TRF2, POT1, TIN2, TPP1 and RAP1, together called the shelterin complex, bind the repeats and hide the chromosome end from the repair machinery. Without shelterin, the cell reads a natural chromosome terminus as a double-strand break and tries to fuse it to another chromosome, producing the end-to-end fusions and breakage cycles that characterize genomic crisis.
What matters is the capping function, not the length as such. A telomere can be long and dysfunctional if shelterin is disrupted, and short telomeres in a cell with intact capping may not signal damage until a threshold is crossed. Average telomere length is therefore only indirectly related to cellular behaviour: the shortest telomere in a cell, not the mean, determines when arrest occurs.
The end-replication problem and the Hayflick limit
DNA polymerase cannot replicate the extreme 5′ end of a lagging strand, so each round of replication removes a small stretch of terminal sequence. James Watson described the geometry of this in 1972. Alexey Olovnikov independently proposed that it would impose a division counter on somatic cells and would explain the replicative limit Leonard Hayflick had observed in cultured human fibroblasts.1 Human somatic cells in culture typically manage a few dozen population doublings before arresting.
Introducing the catalytic subunit of telomerase into normal human cells prevents that arrest and allows indefinite proliferation, which confirmed the causal link between telomere maintenance and the replicative limit.2 Most immortalized cell lines used in research rest on this, and telomerase reactivation is part of what lets induced pluripotent stem cells proliferate without limit.
Telomerase
-
1978Telomere sequence determinedElizabeth Blackburn and Joseph Gall identify the repeated sequence at the chromosome ends of the ciliate Tetrahymena.
-
1985Telomerase identifiedCarol Greider and Blackburn detect an enzyme activity in Tetrahymena extracts that adds telomeric repeats to chromosome ends.
-
1998Human cells immortalizedBodnar and colleagues show that expressing hTERT in normal human cells extends their replicative lifespan indefinitely.
-
2009Nobel PrizeBlackburn, Greider and Jack Szostak share the prize in Physiology or Medicine for the discovery of telomeres and telomerase.
-
2024Telomerase inhibitor approvedImetelstat, which targets the telomerase RNA template, is approved in the United States for anaemia in lower-risk myelodysplastic syndromes.
Telomerase is a ribonucleoprotein in which the protein subunit TERT copies a template carried within the RNA subunit TERC. It is active in germ cells and embryonic stem cells, and at lower levels in adult stem and progenitor compartments and in activated lymphocytes. Most differentiated human somatic cells express little or none, which is why they age replicatively.
Loss-of-function mutations in telomerase components and in shelterin cause the short telomere syndromes, a spectrum that includes dyskeratosis congenita, aplastic anaemia and a substantial fraction of familial idiopathic pulmonary fibrosis.3 These disorders are the cleanest human evidence that telomere maintenance matters. Patients show premature failure of exactly the high-turnover tissues that depend on it, which ties the mechanism directly to stem cell exhaustion. They do not show that ordinary aging is driven by telomeres, since only a subset of tissues is affected and the phenotype is not general.
A weak biomarker
Average leukocyte telomere length is easy to sell as a measure of Biological age and difficult to defend as one. At any given chronological age, variation between individuals is large relative to the average annual rate of loss, so a single measurement says little about an individual. Measurement methods disagree. Quantitative PCR, the cheapest approach and the one behind most consumer tests, has poor within-sample reproducibility compared with terminal restriction fragment analysis or flow-FISH, and results are not comparable across laboratories. Longitudinal studies sometimes report telomeres lengthening in individuals over the follow-up interval, a strong sign of measurement noise.
ContestedConsumer telomere tests, sold through the same direct-to-consumer testing channels as broad blood panels, report a length and an implied "cellular age". No professional body endorses telomere length as a clinical measure of aging outside the diagnosis of telomere biology disorders, and in most head-to-head comparisons methylation-based clocks outperform it as mortality predictors.
Associations between telomere length and lifestyle factors such as physical activity or stress have been widely reported. They are generally small, inconsistently replicated and vulnerable to confounding. The field's own retrospective assessment is that small samples and selective reporting inflated the early effect sizes, a pattern common across candidate aging biomarkers.
The cancer tradeoff
The large majority of human cancers reactivate telomerase, most often through mutations in the TERT promoter that create new transcription factor binding sites. The rest maintain telomeres through a recombination-based mechanism called alternative lengthening of telomeres. Unlimited division requires a solution to the end-replication problem, so in long-lived, large-bodied species telomere attrition is a genuine barrier against tumours.
That makes telomerase therapy for aging structurally awkward. Mendelian randomization studies using genetic variants that raise telomere length find increased risk of several cancers, glioma and melanoma among them, alongside modestly reduced risk of some non-neoplastic conditions.4 Germline POT1 mutations that lengthen telomeres cause familial cancer predisposition syndromes. Any intervention that added telomere reserve across the body would be pushing on a trait for which natural selection appears to have settled on a compromise.
Therapeutic attempts
Work in mice has been more encouraging than the cancer argument would suggest, with a caveat: laboratory mice have very long telomeres and constitutive telomerase in many tissues, which makes them a poor model for the human situation. Systemic delivery of a Tert transgene to adult mice using an adeno-associated viral vector extended median lifespan and improved several health measures without an observed increase in cancer incidence.5 Similar work in cancer-resistant mouse backgrounds also extended lifespan.
The human record is thinner and less reputable. Supplements marketed as telomerase activators, mainly cycloastragenol derivatives, rest on small studies with weak endpoints and are sold under the rules that govern supplements rather than as drugs. At least one biotechnology executive has publicized self-experimental telomerase gene therapy outside clinical trials, with self-reported telomere measurements as the only outcome and no independent verification. Meanwhile, pharmaceutical use of telomere biology has gone the other way: the first approved drug in the area inhibits telomerase to treat a haematological malignancy.
Open problems
The comparative biology does not fit a simple story. Mice have far longer telomeres than humans and live roughly two years. Some negligibly senescent species maintain telomerase in somatic tissue and control cancer by other means. It is not resolved whether telomere attrition contributes materially to the course of normal human aging or only sets a limit in specific high-turnover compartments. The answer bears directly on how much of the damage-repair agenda and the geroscience programme should go to telomeres. The one point of agreement is that raising telomerase everywhere is not a plausible route to extended maximum lifespan without a solution to the cancer problem, and no such solution exists.
See also
- Cellular senescence
- Hallmarks of aging
- Epigenetic clocks
- Aging biomarkers
- Gene therapy for aging
- Negligible senescence
References
Footnotes
-
paperOlovnikov, A. M. "A theory of marginotomy: The incomplete copying of template margin in enzymic synthesis of polynucleotides and biological significance of the phenomenon." Journal of Theoretical Biology, 1973. ↩
-
paperBodnar, A. G. et al. "Extension of life-span by introduction of telomerase into normal human cells." Science, 1998.↩Human cells in culture; extending a cell line's replicative capacity says nothing about the lifespan of an organism.
-
paperArmanios, M., Blackburn, E. H. "The telomere syndromes." Nature Reviews Genetics, 2012. ↩
-
paperTelomeres Mendelian Randomization Collaboration. "Association between telomere length and risk of cancer and non-neoplastic diseases: A Mendelian randomization study." JAMA Oncology, 2017.↩Estimates the effect of lifelong inherited differences in telomere length, which is not the same as the effect of lengthening telomeres in an adult.
-
paperBernardes de Jesus, B. et al. "Telomerase gene therapy in adult and old mice delays aging and increases longevity without increasing cancer." EMBO Molecular Medicine, 2012.↩Mice. The absence of extra cancer was an observation within a lifespan study, not the output of a dedicated carcinogenicity test.